7 Tips on How to Choose Beds for ICU Environments?

Time:2026-10-15 Author:Henry
0%

Choosing an ICU bed is a clinical, operational, and human decision. It affects patient positioning, pressure injury prevention, emergency access, cleaning, and staff safety. That is why how to choose beds for ICU environments should begin with real workflow, not attractive specifications.

Dr. Don Berwick, a leading authority in healthcare quality, said, “Every system is perfectly designed to get the results it gets.” His observation applies directly to ICU equipment selection. A bed with advanced functions may still fail if nurses cannot adjust it quickly, cleaners cannot reach hidden surfaces, or engineers cannot obtain replacement parts. Small details matter. Brake pedals. Scale accuracy. Mattress seams. Alarm visibility.

Experience should guide the evaluation. Observe patient transfers during busy shifts. Ask nurses to perform common adjustments while wearing gloves. Test the bed beside ventilators, infusion pumps, and imaging equipment. Measure turning space around it. Record cleaning time. These practical checks often reveal weaknesses that brochures hide.

Safety remains central. Look for stable braking, safe side rails, emergency positioning, reliable weighing, and clear control systems. Consider patient height, body weight, mobility, and expected length of stay. Also review training needs, preventive maintenance, warranty coverage, and local service capacity.

There is no perfect bed. That is worth admitting. A feature-rich model may increase complexity, cost, or repair demands. A simpler model may serve one unit better. The strongest choice balances patient outcomes, caregiver workload, infection-control practice, durability, and total ownership cost. The following seven tips provide a structured way to compare beds with evidence, humility, and the realities of ICU care.
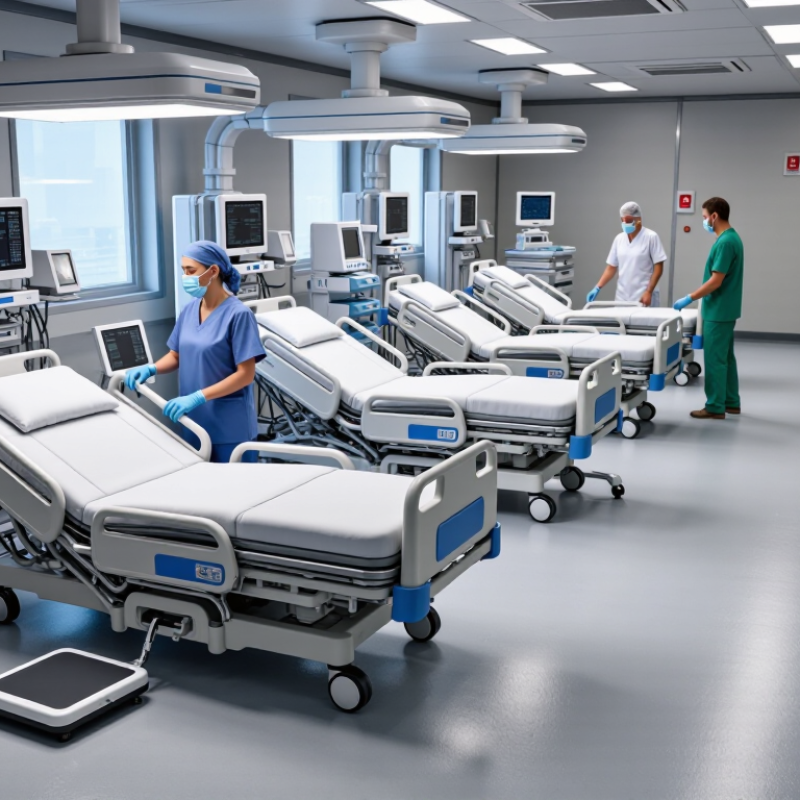
7 Tips on How to Choose Beds for ICU Environments?

Define the Clinical Needs of the ICU Bed

Defining the clinical need should come before comparing ICU bed features. A bed for a ventilated patient needs stable positioning, rapid height adjustment, and clear access for airway care. Patients with severe edema or obesity may require higher safe working loads and wider platforms. AHRQ reports that pressure injuries affect more than 2.5 million U.S. patients each year. Therefore, pressure redistribution, moisture control, and regular repositioning support should be assessed together.

Tip: Ask bedside nurses to describe a difficult shift. Can staff perform lateral transfers without excessive lifting? Can clinicians reach the patient during an emergency? The International Safe Patient Handling & Mobility standards emphasize equipment that reduces caregiver injury risk. Bed height, locking casters, brake visibility, and control placement deserve practical testing. A specification sheet cannot show every problem.

Tip: Match functions to patient pathways. A cardiac ICU may prioritize continuous monitoring access and emergency positioning. A respiratory ICU may need strong head elevation control and removable sections. Infection prevention teams should inspect mattress seams, rails, and electronic controls. The CDC’s environmental infection-control guidance supports cleanable, intact surfaces. I would not assume more functions mean better care. Extra controls can confuse users, especially during alarms. A small usability trial may reveal that uncomfortable truth. A checklist helps, but it can still miss the night shift’s reality.

Assess Patient Safety and Positioning Features

7 Tips on How to Choose Beds for ICU Environments

Tip 1: Check patient positioning controls. The bed should support safe head elevation, knee flexion, lateral movement, and rapid CPR positioning. Controls must be clear, lockable, and reachable by trained staff.

Tip 2: Assess the lowest height. A low platform can reduce injury risk during transfers and accidental falls. Confirm that wheels lock firmly on uneven flooring. Small details matter.

Tip 3: Examine side rails and gap protection. Rails should assist repositioning without creating avoidable entrapment spaces. Their movement should feel smooth, but not loose.

Tip 4: Match the mattress with the bed frame and patient needs. Pressure-redistribution surfaces may help reduce skin damage, but they cannot replace regular skin checks.

Tip 5: Verify stability during turning, transport, and emergency procedures. A bed that shifts slightly can undermine staff confidence and patient safety.

Tip 6: Review alarms, brakes, and power backup features. Audible alerts should be noticeable without causing unnecessary alarm fatigue. Test them during routine inspections.

Tip 7: Consider cleaning access and infection-control procedures. Smooth surfaces, sealed controls, and removable components can simplify disinfection. They are easy to overlook.

A feature-rich bed is not automatically safer. Clinical teams should test the bed with real workflows, different patient sizes, and protective equipment. Written specifications help, but hands-on evaluation often reveals problems that brochures miss.

Compare Infection Control and Cleaning Requirements

7 Tips on How to Choose Beds for ICU Environments?

Compare Infection Control and Cleaning Requirements

In ICU care, bed selection should begin with infection-control details, not appearance. Check whether the mattress platform has sealed edges, smooth surfaces, and minimal exposed joints. Crevices can hold blood, moisture, and disinfectant residue. That is a real cleaning problem. Choose materials that tolerate the hospital’s approved disinfectants without cracking, discoloring, or becoming sticky. A damaged surface may look minor, yet it can become difficult to decontaminate.

Compare every cleaning zone, including side rails, brake pedals, control panels, wheels, and mattress seams. Removable components can support deeper cleaning, but only when staff can reinstall them correctly. Large gaps under the frame may help access, while complex hinges may slow terminal disinfection. Ask for documented cleaning instructions and chemical-compatibility data. Do not rely only on sales demonstrations. A spotless sample bed does not represent a crowded ICU room.

Practical testing matters. Watch staff clean the bed after a simulated spill. Time the process. Note where cloths snag, where water collects, and whether controls remain usable afterward. Infection-control teams should review the design with nurses, technicians, and environmental-services workers. Maintenance access also matters because worn casters, torn covers, and loose rails require prompt attention. Some requirements may conflict: extra mechanisms can improve positioning but create more surfaces to disinfect. That trade-off deserves honest review. A safer choice is not always the most sophisticated one.

7 Tips on How to Choose Beds for ICU Environments? – Compare Infection Control and Cleaning Requirements

Tip Selection Dimension What to Look For Infection-Control Value Cleaning and Disinfection Requirements Acceptance Check
1 Choose a sealed, cleanable mattress system Select a pressure-redistributing mattress with a fluid-resistant, welded-seam cover. The cover should be removable or replaceable and compatible with the facility’s disinfectants. An intact, non-absorbent cover limits penetration of blood, body fluids, and microorganisms into the mattress core. Clean and disinfect after contamination and between patients according to the manufacturer’s validated instructions. Inspect seams, zippers, corners, and the underside for tears or fluid ingress. Review cover material, seam construction, chemical compatibility, contact time, and replacement criteria.
2 Minimize exposed crevices and fluid traps Prefer smooth, continuous surfaces, rounded edges, enclosed mechanisms, sealed joints, and minimal exposed fasteners around the mattress platform and frame. Fewer inaccessible areas reduce locations where organic soil and microorganisms can remain after routine cleaning. The design should permit direct access with a cleaning cloth to the head, foot, side, and lower frame areas without extensive disassembly. Conduct a visual inspection with the bed in flat, raised, and tilted positions; document any inaccessible zones.
3 Evaluate side rails and control surfaces Choose side rails with smooth, sealed surfaces and limited hinges or cavities. Patient and staff controls should be wipeable, sealed, and easy to remove or replace when permitted. High-touch components can transfer contamination between caregivers, patients, and equipment if they are difficult to disinfect. Confirm compatibility with the hospital disinfectant and the required wet contact time. Avoid materials that crack, become sticky, or discolor after repeated use. Test cleaning access around hinges, release handles, nurse controls, handset holders, and cable interfaces.
4 Confirm compatibility with hospital disinfectants Obtain a written compatibility list covering the frame, mattress cover, side rails, casters, plastics, screens, and accessories used with the bed. Material damage can create cracks, rough surfaces, peeling coatings, or failed seals that retain soil and moisture. The cleaning protocol must state the approved product, dilution or concentration, application method, wet contact time, rinsing needs, and drying instructions. Compare the protocol with disinfectants actually used by environmental-services staff, not only products listed in sales literature.
5 Check mobility and clearance for thorough cleaning Look for stable casters, reliable brakes, sufficient clearance beneath the frame, and a design that can be moved safely away from walls and equipment. Improved access helps staff clean high-touch areas and floors around and beneath the bed, where dust and contaminated fluids may accumulate. The bed should allow routine cleaning without unsafe lifting or improvised positioning. Caster housings and brake pedals should be accessible for wiping. Perform a timed cleaning trial in a representative ICU room using the facility’s normal equipment and workflow.
6 Assess removable accessories and equipment interfaces Select IV-pole mounts, drainage-bag holders, mattress retainers, over-bed tables, and monitor supports that can be detached or fully accessed for cleaning. Accessories and attachment points can become overlooked reservoirs when they are permanently fixed or crowded with cables and tubing. Define which accessories remain with the bed, which are cleaned separately, and how staff should manage cables, tubing, and removable components during terminal cleaning. Request a component-level cleaning map and verify that every detachable part has an identification and reassembly procedure.
7 Verify documentation, training, and lifecycle support Require clear user instructions, cleaning checklists, preventive-maintenance guidance, replacement-part availability, and training for nursing and environmental-services teams. Consistent procedures reduce variation in cleaning practice and help staff identify damaged surfaces before they become difficult to decontaminate. Documentation should distinguish routine cleaning, discharge or terminal cleaning, spill response, mattress-cover replacement, and maintenance isolation. Pilot the bed with infection-prevention, nursing, facilities, and environmental-services representatives before purchase.
Practical evaluation note: Cleaning effectiveness depends on the bed design, the disinfectant label, required wet contact time, staff training, and adherence to the facility’s infection-prevention policy. Always validate the final cleaning procedure with the infection-prevention and environmental-services teams.

Review Mobility, Monitoring, and Equipment Compatibility

Choosing an ICU bed is a safety decision, not a furniture purchase. WHO’s Global Patient Safety Report 2024 estimates that one in ten patients experiences harm during healthcare. Bed design can reduce avoidable risks.

Use seven practical checks. Confirm low-height positioning, strong brakes, and smooth steering for bedside mobility. Check the safe working load, including the patient and attached equipment. Test transfer spaces with a lift and wheelchair. Verify that imaging access matches local workflows. Inspect cable routing around monitors, infusion pumps, and ventilators. Ensure alarms remain visible and audible from normal staff positions. Finally, confirm electrical and mechanical compatibility with existing equipment.

Mobility should feel controlled, not forced. The 2018 SCCM PADIS guidelines support rehabilitation and mobilization interventions for suitable adult ICU patients. A narrow turning radius and secure side rails can help, but staff must test them with real devices. The 2023 ECRI Health Technology Hazards report continues to identify alarm management as a major patient-safety concern. A bed that blocks alarms is unsuitable, even if it looks advanced. Our own early checklist missed cable length and floor thresholds. That was a useful failure. Invite nurses, physiotherapists, biomedical engineers, and infection-control staff to test a sample bed during realistic scenarios. Document failures, not only successful demonstrations.

7 Tips for Choosing Beds for ICU Environments

Recommended evaluation emphasis for mobility, monitoring, patient safety, and equipment compatibility.

Use this 100-point checklist to compare ICU beds consistently. Prioritize safe patient handling, clear access for monitoring, compatibility with ventilators and infusion pumps, reliable mobility controls, infection-prevention features, and staff workflow. Always verify the final specifications against local clinical requirements and applicable safety standards.

Evaluate Durability, Usability, and Total Cost of Ownership

Choosing ICU beds requires more than comparing purchase prices. Start by checking frame strength, safe working load, and cycle testing records. A bed should remain stable during frequent repositioning. Inspect welds, casters, rails, and electrical cables. Small failures become serious during a night shift. Also review cleaning compatibility. Harsh disinfectants can damage plastics, labels, and moving joints over time.

Usability affects every bedside action. Test the controls while wearing gloves. Confirm that key functions are visible and easy to operate. Check brake pedals, emergency positioning, height adjustment, and patient transfer clearance. Listen for unusual motor noise. Ask nurses to move the bed through a narrow doorway. Their practical experience often reveals problems that specifications miss. We once underestimated the value of a simple control layout. That was a costly lesson.

Total cost of ownership includes delivery, installation, training, maintenance, replacement parts, energy use, and downtime. Request service intervals and expected component life in writing. Compare warranty coverage carefully. A cheaper bed may need more frequent repairs or specialized technicians. Calculate the cost of unavailable beds during peak demand. Consider washable accessories and standardized parts. They can reduce inventory pressure. Do not ignore staff time. An awkward bed may add minutes to every patient transfer. Over a year, those minutes become a measurable operational cost. Perfect forecasts are impossible, so leave room for repair delays and changing clinical needs.

FAQS

What clinical needs should an ICU bed address?

It should support stable positioning, quick height adjustment, airway access, and emergency care. Patient size matters. Wider platforms may help larger patients.

How can a team test bedside mobility?

Ask nurses to move the bed through a narrow doorway. Test brakes, steering, turning space, and transfer clearance with real equipment. Specifications cannot show every obstacle.

What safety features deserve practical testing?

Check low-height positioning, visible brakes, secure rails, and accessible controls. Confirm the safe working load includes the patient and attached devices. Test emergency positioning.

How should the bed support pressure injury prevention?

Assess pressure redistribution, moisture control, and repositioning support together. Check mattress seams and surfaces for cleanability. A feature list is not enough.

How can staff evaluate alarms and cables?

Place monitors, pumps, and ventilators as they appear during a real shift. Confirm cables do not restrict movement. Alarms must remain visible and audible.

What makes an ICU bed easy to use?

Controls should be clear through gloves. Brake pedals, height adjustment, and emergency functions need quick access. Simple layouts often reduce confusion.

How should durability be assessed?

Inspect welds, casters, rails, cables, and moving joints. Review cycle-testing records and component life. Listen for unusual motor noise. Small failures become serious overnight.

What costs belong in total ownership calculations?

Include delivery, installation, training, maintenance, parts, energy, repairs, and downtime. Staff time also matters. A slow transfer can add minutes every day.

Who should participate in a bed evaluation?

Invite nurses, physiotherapists, biomedical engineers, and infection-control staff. Use realistic scenarios, including night-shift conditions. Document failures, not only successful demonstrations.

Conclusion

Choosing an ICU bed requires a careful balance between clinical performance, patient safety, staff efficiency, and long-term value. To understand how to choose beds for ICU environments, begin by identifying the unit’s clinical needs, including patient acuity, treatment procedures, and the level of repositioning or support required. Safety features such as secure side rails, stable positioning, fall prevention, and pressure redistribution should also be assessed to protect patients and support recovery.

Infection control is equally important, so the bed should have smooth, accessible surfaces, durable materials, and components that can be cleaned and disinfected efficiently. Consider whether the bed supports patient mobility, integrates with monitoring devices and medical equipment, and allows caregivers to work comfortably. Finally, evaluate construction quality, ease of operation, maintenance requirements, expected service life, and total cost of ownership. A well-selected ICU bed should provide reliable performance, practical usability, and adaptable support for both patients and healthcare professionals.

Henry

Henry

Henry is a dedicated marketing professional with a profound expertise in the company's offerings. With years of experience in the industry, he possesses an impressive understanding of the market dynamics and consumer behaviors that drive success. Henry is committed to sharing his insights through......